What the Anion Gap Evaluates in Critical Care
The anion gap is a rapid, practical way to measure the acid-base state using routine electrolytes from the serum chemistry panel. In critical care, it helps identify an underlying metabolic acidosis and supports early cause identification when a patient is deteriorating, ventilated, septic, or otherwise physiologically stressed.
An anion gap calculator is helpful because it translates a standard lab pattern into bedside action. Rather than considering sodium, chloride, and bicarbonate as isolated values, the clinician can read them together as a marker of an acidotic state, anion deficit, or broader metabolic derangement. That makes the result valuable for diagnostic support and risk stratification.
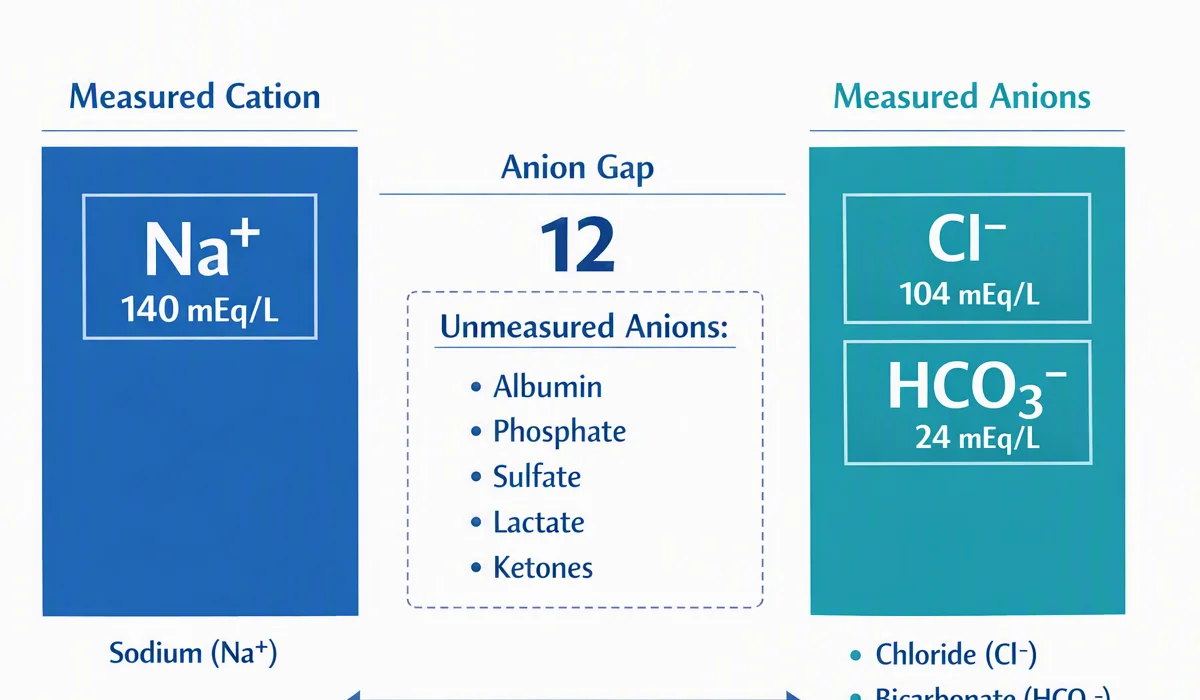
Physiologically, the anion gap reflects the difference between measured cations and measured anions in the bloodstream. Unmeasured anions such as lactate, ketones, and certain toxins can build up, altering acid-base balance. In contrast, changes in chloride can hide a problem and produce a normal anion gap even when acidosis is present. Because of that, clinical interpretation must always consider the full laboratory result and the bedside context.
For critical care, the anion gap is not a stand-alone diagnosis. It is a screening clue that often points toward lactic acidosis, ketoacidosis, renal failure, or toxic ingestion. It can also help differentiate a primary acid-base disorder from a compensatory response. Used well, it becomes part of a systematic approach to acid-base disorder recognition.
How to Use an Anion Gap Calculator
An anion gap calculator relies on a basic anion gap formula using routinely ordered serum values. The usual calculation is:
Anion gap = serum sodium - (serum chloride + serum bicarbonate)
Some labs or clinicians may apply alternative formulas that include potassium, but the sodium-based version is the standard for bedside assessment. The important part is to apply the same method consistently and interpret the laboratory result in the context of the reference interval used by that lab.
Because the calculation is built from sodium, chloride, and bicarbonate, it is often available whenever an electrolyte panel is ordered. That makes it an efficient tool for rapid clinical interpretation in critical care, especially when a patient is deteriorating and immediate trend monitoring matters.
Step-by-Step Calculation Inputs
To use the calculator correctly, enter the following values from the patient’s serum chemistry:
- Serum sodium: the sodium level that is measured Serum chloride: the measured chloride concentration Serum bicarbonate: the measured bicarbonate concentration or total CO2, depending on the lab
Once these are entered, the calculator determines the anion gap automatically. Practically, this is a quick bedside workflow: review the electrolyte panel, confirm units, and calculate the gap before moving to broader diagnostic support. If the patient has severe illness, the number should be interpreted alongside other signs of perfusion, ventilation, and organ function.
A key nuance is that serum bicarbonate may be altered by respiratory compensation or prior treatment. Therefore, the number should not be interpreted in isolation. It reflects the current serum chemistry pattern, but the broader acid-base disorder may be more complex.
Interpreting the Result at the Bedside
Interpreting the result begins with the normal range used by the laboratory. Although the exact reference interval can vary, a typical range is often around 8 to 12 mEq/L without potassium or slightly higher with different methods. Because laboratory variation exists, the clinician should always rely on the local reference interval rather than a memorized value alone.
A high anion gap indicates accumulation of undetected anions and strengthens the diagnosis of acidic metabolic disturbance. This is especially important in intensive care, where elevated lactate, ketones, renal dysfunction, or toxic ingestion may require immediate intervention.
A reduced anion gap is rarer, but it can still matter. It may reflect hypoalbuminemia, laboratory variation, paraproteinemia, or uncommon measurement issues. In some cases, a low value is a clue that the apparent acid-base balance is being distorted by changes in albumin or other serum proteins.
Point-of-care interpretation should answer three questions: Is there an abnormal gap? Is there evidence of metabolic acidosis? And does the result indicate a single process or a mixed acid-base disorder? That framework converts a number into actionable clinical interpretation.
Adjusting the Anion Gap for Protein
Because albumin is a important unmeasured anion, low albumin can make the anion gap appear artificially normal or only mildly elevated. This is why albumin correction is vital in acute care, where hypoalbuminemia is frequent due to inflammation, fluid shifts, dilution, and illness severity.
The corrected anion gap takes into account hypoalbuminemia and helps identify hidden acidosis. If the patient’s albumin is low, the measured gap may miss the true burden of unmeasured anions. That means, a “normal” number can mask a clinically important acidotic state.
Some institutions may use alternative correction factors, but the core idea is the same: lower albumin lowers the expected anion gap. When albumin is reduced, adding a correction term can improve risk stratification and sharpen cause identification. This is especially useful when evaluating sepsis, shock, malnutrition, cirrhosis, or prolonged critical illness.
When applying albumin correction, always assess the result with the full clinical picture. A corrected anion gap can reclassify a patient from normal anion gap to high anion gap metabolic acidosis, which may affect the workup and urgency of care. This https://anion-gap-calculator330.image-perth.org/can-metformin-trigger-a-high-anion-gap is why albumin should be checked whenever the numbers and the bedside picture do not match.
High Anion Gap Metabolic Acidosis: Key Causes
A high anion gap suggests excess unmeasured acids in the blood and is a typical sign of metabolic acidosis. In acute care, the leading causes often appear quickly during bedside assessment because they are tied to shock, impaired perfusion, or acute metabolic stress.
Lactic acidosis is one of the most important causes. It may occur with sepsis, hypoperfusion, hypoxemia, seizures, or medication-related metabolic derangement. An elevated lactate should trigger immediate evaluation of circulation, oxygen delivery, and source control when appropriate.
Ketoacidosis is another major cause, including diabetic ketoacidosis, starvation ketosis, and alcoholic ketoacidosis. These states create a high anion gap through accumulation of organic acids. In the ICU, the history, glucose pattern, and ketone measurements help narrow the cause.
Renal failure can produce high anion gap acidosis by limiting acid excretion and allowing unmeasured acids to accumulate. This can develop acutely or worsen on top of chronic kidney disease. Worsening creatinine, oliguria, and electrolyte shifts often reinforce the diagnosis.
Toxins must also be considered, especially in unexplained or severe cases. Toxic ingestion may involve salicylates, toxic alcohols, or other agents that create a marked metabolic acidosis. When the history is unclear, the gap can provide an early clue that life-threatening exposure is present.
In practice, a high gap should trigger prompt evaluation of perfusion, oxygenation, renal function, glucose, ketones, and exposure history. The value itself is not the endpoint; it is a signal to identify the underlying process and respond quickly.
Normal Anion Gap Metabolic Acidosis and Differential Diagnosis Overview
A within-range anion gap does not rule out acidosis. In fact, it often points toward hyperchloremic metabolic acidosis, where bicarbonate is depleted or replaced by chloride, keeping the gap within the reference interval. This presentation is common in critical care and can be as clinically significant as a high gap disorder.
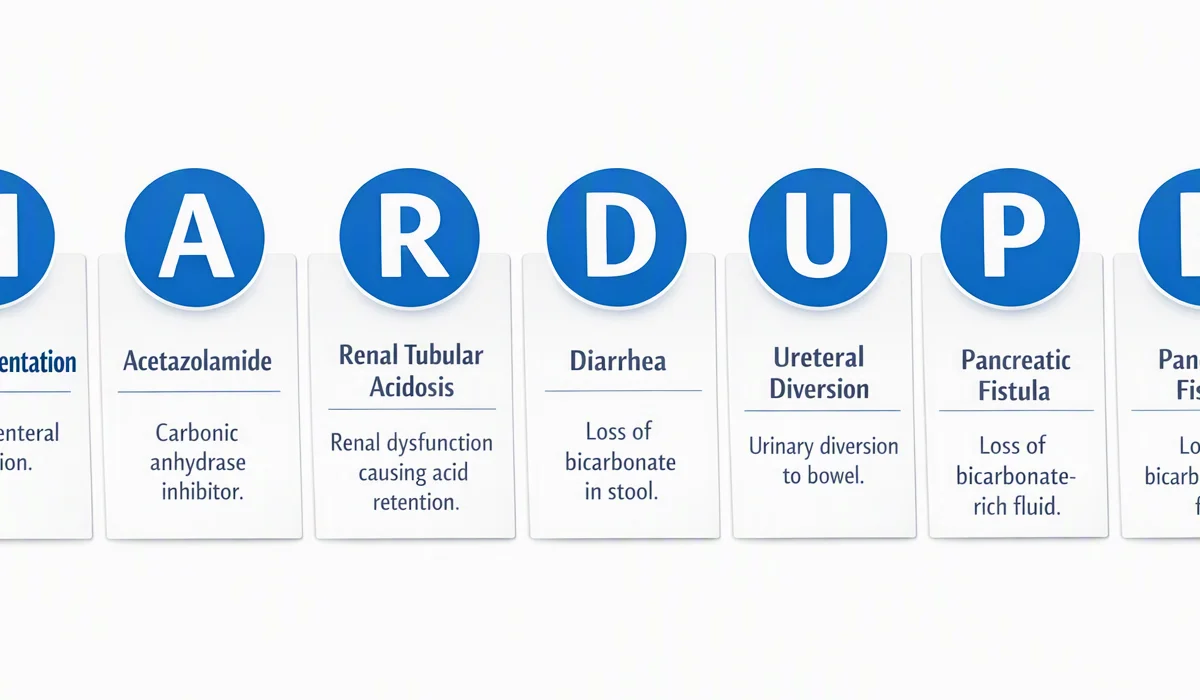
Diarrhea is a classic cause because gastrointestinal bicarbonate loss causes a non-gap acidosis. Large-volume stool losses can swiftly alter acid-base balance, especially when compounded by poor intake, shock, or kidney injury.
RTA is another key diagnosis. It reflects impaired acid handling in the kidneys and may appear with a normal anion gap despite ongoing metabolic acidosis. The clinical context, urine studies, and serum chemistry trends help differentiate renal tubular causes from gastrointestinal bicarbonate loss.
The diagnostic differential for normal gap acidosis also includes iatrogenic chloride load, such as large-volume saline resuscitation, and early renal dysfunction. In critical care, these patterns are often mixed, so the clinician should avoid assuming that a normal anion gap means the problem is limited or resolved.
At the bedside, the main question is whether bicarbonate has fallen because it was lost or because another ion shifted in to keep electroneutrality. That framework helps differentiate hyperchloremic metabolic acidosis from high gap disorders and directs next steps in treatment.

Challenges, Limitations, and Clinical Relevance
Despite that a correctly calculated anion gap can be misleading if the clinical context is not considered. A common problem is laboratory variation. Various analyzers and methods may produce slightly different reference interval boundaries, so the same patient can seem normal in one system and abnormal in another.
Another important limitation is the mixed acid-base disorder. A patient may have both an increased anion gap metabolic acidosis and metabolic alkalosis, or a high gap process plus respiratory compensation that changes the serum bicarbonate. In these cases, the anion gap alone may fail to capture the complexity of the acid-base disorder.
The delta ratio approach is valuable when a high anion gap is present and you want to know whether another process is also occurring. By assessing the rise in anion gap to the fall in bicarbonate, the delta gap can identify hidden metabolic alkalosis or additional non-gap acidosis. This is especially valuable in critical care, where multiple processes often coexist.
Albumin remains one of the most common interfering factors. Low albumin can disguise a major anion deficit, while hemoconcentration can move the result in the opposite direction. Clinical interpretation should therefore pair the electrolyte panel with albumin, renal data, perfusion markers, and bedside examination.
Finally, the anion gap is a tool for diagnostic support, not a standalone answer. It should inform cause identification, prompt serial monitoring, and improve prioritization, but it cannot replace a full acid-base assessment.
When to Retest Labs and Advance Care
Tracking trends is important when the anion gap is elevated or the patient’s condition is shifting. A single test result provides a snapshot, but serial monitoring shows whether the metabolic derangement is gettings better, worsening, or responding to therapy.
Order prompt repeat testing when the patient has shock, severe infection, worsening renal function, altered mental status, persistent tachypnea, or suspected toxic ingestion. In critical care, these are clues that the acid-base balance may shift rapidly and that the original laboratory result may be insufficient.
An arterial blood gas is often useful when the serum chemistry and the bedside picture are not consistent. It helps assess pH, respiratory compensation, oxygenation, and the broader acid-base disorder. Together with the electrolyte panel, it provides a better-rounded view of the patient’s physiology.
Escalate care when the gap is rising, lactate remains elevated, bicarbonate continues to fall, or the clinical status deteriorates despite treatment. A worsening gap in critical illness can indicate ongoing hypoperfusion, inadequate source control, progression of renal failure, or unresolved toxic ingestion. Prompt reevaluation supports timely intervention and safer decision-making.
Common Questions Regarding Anion Gap Calculation
What does an anion gap calculator for?
An anion gap calculator is designed to quickly calculate the anion gap from serum sodium, serum chloride, and serum bicarbonate. In critical care, it helps identify metabolic acidosis, suggest possible causes such as lactic acidosis or ketoacidosis, and support bedside assessment when rapid clinical interpretation is needed.
What is the normal anion gap range?
The normal anion gap range depends on the laboratory reference interval, but many labs report a typical range around 8 to 12 mEq/L when potassium is excluded. Because laboratory variation exists, the most accurate approach is to use the reference range provided with the patient’s result.
How do you correct anion gap for albumin?
To correct the anion gap for albumin, you apply an albumin correction formula that accounts for hypoalbuminemia. Since albumin is an unmeasured anion, low albumin can make the measured gap look lower than it really is. The corrected anion gap gives a better estimate of the true acid-base burden.
Why is there a high anion gap in critical care patients?
Common causes of a high anion gap in critical care include lactic acidosis, ketoacidosis, renal failure, and toxins. These conditions increase unmeasured acids in the blood and often require urgent evaluation. The anion gap should be interpreted alongside the clinical picture, lactate, ketones, kidney function, and any concern for toxic ingestion.
Can a normal anion gap still indicate metabolic acidosis?
Yes. A normal anion gap can still indicate metabolic acidosis, especially hyperchloremic metabolic acidosis. This pattern may occur with diarrhea, renal tubular acidosis, or chloride-rich fluid administration. A normal gap does not rule out acid-base disorder; it only suggests that the type of acidosis may be different.