What the Anion Gap Indicates
The anion gap is a calculated value that assists clinicians in interpreting an electrolyte panel by examining the balance between measured plasma ions. It is not directly reported on most lab results, but it can be calculated from the numbers that are already present in routine testing. Because it reflects the difference between major measured cations and anions, it provides an important window into acid-base balance.
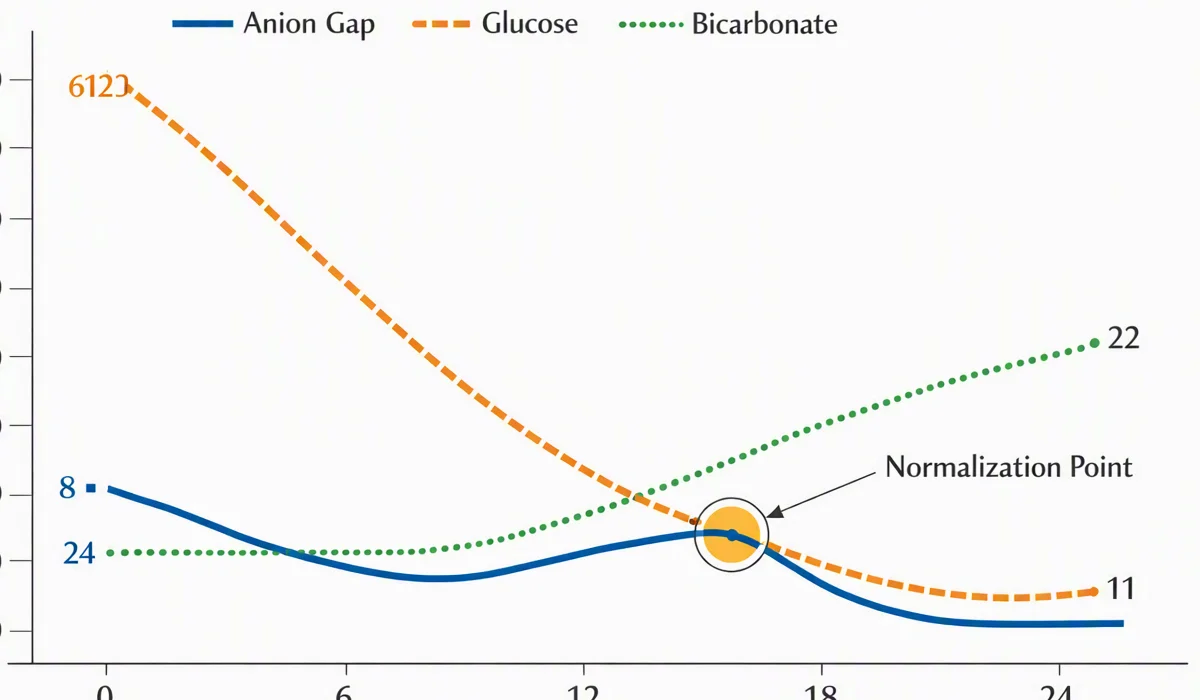
An high or unexpectedly low result can serve as a diagnostic clue when reviewing lab results. In practice, the anion gap is most helpful for recognizing an acid-base disorder, especially metabolic acidosis. It also aids broader clinical interpretation of electrolyte values by indicating hidden acid accumulation, unmeasured ions, or a shift in protein-related charge balance.
An anion gap calculator makes easier this process by turning routine measurements into a quick gap analysis. That can be especially useful when a clinician is reviewing an electrolyte imbalance or trying to connect a chemistry panel with the patient’s symptoms, history, and possible toxin exposure.
Anion Gap Calculator Formula and Values
The main computational formula relies on the most common blood electrolytes: sodium, chloride, and bicarbonate. In many cases, potassium may also be included, although the simplified formula often excludes it.
A common version is:
Anion gap = sodium − (chloride + bicarbonate)
In versions that include potassium, the formula becomes:
Anion gap = sodium + potassium − (chloride + bicarbonate)
The precise version used can vary depending on the lab and the reference interval used for interpretation. That is why an anion gap calculator should always be paired with the lab’s own reporting conventions and the patient’s overall condition.
These inputs are important because they reflect the major measured ions in the sample. Serum sodium represents the dominant measured cation, while serum chloride and serum bicarbonate are major measured anions. The resulting number estimates the amount of unmeasured anions in the blood, which can signal acid accumulation or a shift in protein binding.
How to Work Out Anion Gap Step by Step
To determine the anion gap, start with the serum electrolytes from a latest chemistry panel. Most commonly, these results come from a basic metabolic panel or a comprehensive metabolic panel. Then use the formula with the numbers reported for sodium, chloride, and bicarbonate.
In order, the process goes like this:
- Note the reported sodium value. Identify the chloride value. Identify the bicarbonate value. Add chloride and bicarbonate together. Take away that total from sodium.
For instance, if sodium is 140, chloride is 102, and bicarbonate is 24, the calculation is 140 − (102 + 24) = 14. This result can then be compared against the local normal range.
If potassium is part of the formula used by a specific lab or tool, add it in the sodium side of the equation. Since different panels may report values in slightly different units or formats, unit conversion should always be checked before interpreting the result. A small mismatch in units can create a misleading answer even when the calculation formula is applied correctly.
In clinical use, the calculation is quick, but interpretation is more important than the number alone. The anion gap should be viewed in relation with the full set of electrolyte values, the patient’s symptoms, and any sign of an acid-base disorder.
Normal Anion Gap Compared to Elevated Anion Gap
A typical anion gap usually means the gap between measured cations and anions falls within the expected normal range. That does not always mean the patient is well, but it implies there is no obvious increase in unmeasured acids based on the panel alone.
A high anion gap often points to acidosis. In https://anion-gap-reader906.quillnesty.com/posts/anion-gap-calculator-with-adjusted-chloride-formula this setting, extra acids accumulate in the body, bicarbonate is consumed as it buffers those acids, and the gap rises because the unmeasured anions increase. This is why the anion gap is such a important helpful sign when analyzing lab results.
In test interpretation, the distinction between normal and high values matters because it guides the next step in evaluation. A high result may prompt review for acid overload, kidney dysfunction, or toxin ingestion. A normal result may shift attention toward bicarbonate loss or chloride gain. Either pattern can reflect a significant metabolic derangement.
Frequent Reasons of a High Anion Gap
A high result is commonly linked to a number of important conditions. One of the best-known causes is lactic acidosis, in which lactate rises when tissues are poorly perfused or when metabolism is altered. Another major cause is ketoacidosis, where ketone bodies accumulate during insulin deficiency, starvation, or severe metabolic stress.
Renal failure can also increase the anion gap because impaired kidneys cannot clear acids efficiently. As renal function declines, acid retention contributes to acid accumulation and a declining metabolic picture. This is one reason the anion gap is commonly reviewed alongside kidney-related chemistry findings.
Toxic alcohols are another important cause. Ingestion of substances such as methanol or ethylene glycol can lead to severe acid-base changes and a dangerously high gap. In this setting, the anion gap becomes a major sign of possible toxin exposure and may require urgent evaluation.
Other high-gap conditions exist as well, but these four are among the key clinical factors. A careful review of the history, symptoms, and lab results helps determine whether the elevated number is due to poor perfusion, ketone production, renal impairment, or a toxic ingestion.
Typical Causes of a Normal Anion Gap
A normal anion gap cannot rule out a major problem. It may instead suggest a separate type of acid-base imbalance, especially one driven by bicarbonate loss rather than acid excess. One common cause is diarrhea, which can lead to considerable loss of bicarbonate from the digestive tract.
Renal tubular acidosis is another significant cause. In this condition, the kidneys cannot process acid and bicarbonate correctly, leading to a pattern that often shows a normal anion gap despite ongoing metabolic problems. The issue may be subtle, but the chemistry pattern is a strong clue.
Loss of bicarbonate from any source can produce this pattern, and that makes bicarbonate depletion central to the interpretation. To keep electrical neutrality, the body often keeps chloride, which leads to hyperchloremia. The result is a normal anion gap with a changed chloride-bicarbonate relationship.
This pattern is sometimes described as hyperchloremic metabolic acidosis. Even though the anion gap remains in range, the patient may still have a important acid-base problem that needs attention.
Modified Anion Gap and Albumin
Albumin is as one of the key unmeasured anions in blood, so its concentration can greatly affect the anion gap. When albumin is low, the gap may seem deceptively normal or only mildly elevated even if a major acid-base problem is present. For this reason hypoalbuminemia must always be considered during interpretation.
The corrected anion gap adjusts for low albumin and offers a more accurate assessment of the patient’s true acid-base state. This process is often called albumin correction. Without it, clinicians may underestimate the severity of the metabolic disturbance.
The reason is related to protein binding. Albumin bears negative charge in the bloodstream, so when albumin drops, the measured gap can narrow even if other acids are present. Correcting for albumin helps expose hidden abnormalities that might otherwise be missed.
For example, a patient with a apparently normal gap and marked hypoalbuminemia may actually have a clinically significant high-gap process once the correction is applied. For this reason albumin should be reviewed whenever the result does not match the clinical picture.
When is the time to Use an Anion Gap Calculator
An anion gap calculator is most useful as soon as a clinician is reviewing an electrolyte panel for signs of an acid-base imbalance. It can be run to a basic metabolic panel or a comprehensive metabolic panel, both of which usually include the values needed for the calculation.
It is particularly helpful as a form of clinical decision support when the patient has symptoms that could indicate metabolic instability, such as dehydration, altered mental status, unexplained illness, or suspected poisoning. It can also assist in guiding the evaluation of low bicarbonate or other lab abnormalities into a more coherent diagnostic pathway.
Because the calculator provides a fast summary of key serum electrolytes, it can support bedside reasoning and direct follow-up testing. Still, it should not replace clinical context. A numeric result is most useful when interpreted with the full picture of lab findings, history, and physical exam.
Drawbacks and Frequent Calculation Errors
Even though the formula is straightforward, several factors can affect accuracy. Lab variability is one issue, since different analyzers and reporting methods can yield somewhat different values. That means two panels from different labs may differ slightly, even when the patient’s condition has not changed.
The chosen reference range also matters. What counts as normal in one setting may differ in another, especially if the lab uses a different calculation method or includes potassium. This makes it important to evaluate the result using the correct local standard rather than relying on a single universal cutoff.
Measurement error can occur if a sample is mishandled, diluted, or otherwise compromised. In some cases, a lab artifact may create a misleading result that does not reflect the patient’s true physiology. Repeating the test or comparing it with the broader clinical picture can help identify these issues.
One practical pitfall is assuming that a “normal” number always means there is no problem. Another is forgetting to account for albumin, which can hide a substantial gap. Careful review of the full panel and awareness of potential error sources raise the quality of interpretation.
Frequently Asked Questions on Anion Gap Interpretation
What does an anion gap calculator used for?
An anion gap calculator helps to turn an electrolyte panel into a useful estimate of unmeasured ions in the blood. It assists in clinical interpretation of lab results, especially when evaluating metabolic acidosis, acid accumulation, or an unexpected electrolyte imbalance. It is a handy tool for reviewing sodium, chloride, and bicarbonate together.
How can you calculate anion gap from an electrolyte panel?
Apply the calculation formula: sodium minus the sum of chloride and bicarbonate. In some settings, potassium is included as well. The values usually come from serum electrolytes on a basic metabolic panel or comprehensive metabolic panel. After calculating, check the result with the lab’s normal range or reference interval.
How should you interpret a high anion gap mean?
A high anion gap usually suggests metabolic acidosis caused by added acids or unmeasured anions. Common causes include lactic acidosis, ketoacidosis, renal failure, and toxic alcohols. The result is a important indicator that points toward acid accumulation and helps narrow the differential diagnosis.
Why does low albumin affect the anion gap?
Low albumin can lower the measured gap because albumin contributes negative charge in blood. With hypoalbuminemia, the apparent result may underestimate the true disorder. A corrected anion gap uses albumin correction to better reflect the actual acid-base balance and avoid missing important abnormalities.
Can a standard anion gap really indicate a major condition?
Indeed. A typical anion gap can also occur with serious conditions such as diarrhea, renal tubular acidosis, or additional causes of bicarbonate loss. Hyperchloremia may also be seen. So a normal result does not automatically eliminate an acid-base imbalance; it only points to a distinct pattern of disturbance.