
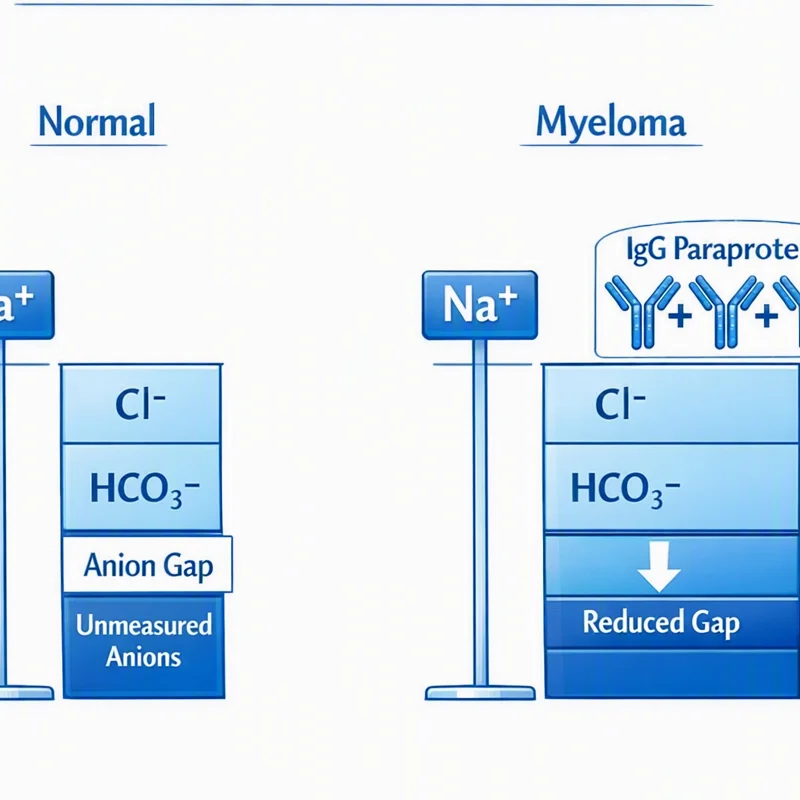
What the Anion Gap Reflects
The anion gap is a basic way to look at the relationship of charged particles in the blood, especially within a routine serum chemistry panel. It helps clinicians identify an acid-base disorder by comparing major measured electrolytes, mainly serum sodium, serum chloride, and bicarbonate. Because many clinically important ions are not directly measured, the anion gap can highlight the presence of unmeasured anions that may be driving an electrolyte imbalance.
At a clinical level, the anion gap acts like a screening tool for hidden acid buildup. If bicarbonate is low, the body may be depleting its main buffer system to neutralize an acid load. In that setting, the anion gap helps separate whether the loss of bicarbonate is being replaced by chloride, which suggests a normal gap pattern, or whether it is being replaced by unmeasured acids, which suggests a widened gap.
The concept is especially useful because the anion deficit may reflect clinically important conditions before they are obvious from symptoms alone. A rising anion gap can point toward problems such as ketoacidosis or lactic acidosis, while a normal gap can suggest bicarbonate loss through the gut or kidneys. This makes the anion gap a key part of clinical decision support and acid-base evaluation.
The Reason Reduced Bicarbonate Level Is Important
Bicarbonate is one of the body’s key safeguards against excess acid. When bicarbonate is reduced, it often means the body is either losing base or burning it to balance acid production. This is why a low bicarbonate value is a central clue in metabolic acidosis, an acid-base disorder that can suggest anything from mild illness to a major metabolic problem.
Many laboratories report bicarbonate as serum CO2 on the chemistry panel. That result is closely related to bicarbonate and is often used as a substitute in routine interpretation. When serum CO2 is low, the clinician should think about whether the patient has actual metabolic acidosis, respiratory compensation, or a mixed disorder. The number alone is not enough; it must be read in context with lab values and the full clinical picture.
Low bicarbonate matters because it can signal either a primary acid problem or compensation for another problem. For example, the body may lower bicarbonate as part of metabolic compensation for an acid-base disturbance, or bicarbonate may be falling because acid is accumulating more quickly than the body can buffer it. The result interpretation depends on whether the anion gap is within normal limits or elevated and whether symptoms, medications, and kidney function match the pattern.
In a practical diagnostic workflow, a low bicarbonate result should prompt a careful review of the acid-base balance rather than a single-number response. That approach reduces missed diagnoses and helps identify the most probable possible causes of the abnormality.
How to Operate an Anion Gap Calculator
An anion gap calculator is a fast way to estimate the anion gap from standard chemistry labs. It typically uses serum sodium, serum chloride, and serum bicarbonate. The calculator is helpful because it organizes the arithmetic and helps with result interpretation when bicarbonate is low.
To use it correctly, enter the current lab values exactly as reported. Most calculators apply the same logic: sodium minus chloride minus bicarbonate. Some versions include potassium, but the sodium-based version is more common in clinical practice. Once the number is generated, compare it with the lab’s reference range and then read it alongside the bicarbonate value.
Here is the basic approach:

- Confirm the serum sodium value. Confirm the serum chloride value. Confirm the serum bicarbonate or serum CO2 value. Calculate the anion gap. Compare the result with the lab’s reference range. Decide whether the pattern suggests a normal gap or high gap acidosis.
Using an anion gap calculator is particularly useful when low bicarbonate is discovered unexpectedly. It supports quick screening, but it should never override clinical judgment. A calculator can identify whether the chemistry pattern points toward a high gap process, but it cannot explain the full cause without additional data such as kidney function, glucose, lactate, or ketones.
For the most accurate reading, make sure the values come from the same sample and that there is no obvious lab inconsistency. Small shifts in electrolytes can change the interpretation, especially if the patient has a mixed acid-base picture.
Anion Gap Calculations and Reference Ranges
The most frequently used anion gap formula is:
anion gap = serum sodium - (serum chloride + serum bicarbonate)
This equation estimates the difference between measured cations and measured anions. This remaining difference reflects unmeasured ions, including protein molecules, phosphates, sulfates, lactate, and various acids. Since albumin is a key unmeasured anion, low albumin can make the anion gap appear incorrectly low or within range even when acid is present.
The normal anion gap differs by laboratory method and analyzer, so always use the reported reference range from the specific lab. In many settings, the range is fairly narrow, but the exact cutoff depends on the measurement technique. For that reason using a calculator should be paired with local lab context rather than a universal cutoff.
Albumin correction is important when albumin is reduced. The albumin-corrected anion gap modifies the result upward to account for the loss of negatively charged albumin. This matters because low albumin can hide a true high gap process. That means a patient may appear to have a normal anion gap when the real picture is a hidden accumulation of acids.
A corrected value gives better laboratory interpretation and improves the accuracy of acid-base evaluation. If albumin is available, it should be reviewed alongside the chemistry panel, especially when bicarbonate is low and the clinical picture is ambiguous.
Understanding Low Bicarbonate With a Normal or High Anion Gap
Low bicarbonate with a normal gap metabolic acidosis usually points to bicarbonate loss or impaired acid secretion without accumulation of unmeasured acids. This pattern is often called hyperchloremic acidosis because chloride goes up to replace the lost bicarbonate. It is a classic example of a chloride shift in the measured electrolytes.
Low bicarbonate with a elevated anion gap metabolic acidosis suggests the presence of unmeasured acids. In this situation, bicarbonate is being consumed while the anion gap widens. Common examples include lactic acidosis, ketoacidosis, and severe kidney dysfunction. The anion gap is especially useful here because it points toward a systemic acid burden rather than simple bicarbonate loss.
Lactic acidosis occurs when lactate builds up due to tissue hypoperfusion, sepsis, hypoxia, medication effects, or other metabolic stressors. Ketoacidosis can appear with diabetes, prolonged fasting, alcohol use, or starvation states. In both cases, the bicarbonate falls because it is buffering excess acid.
Renal failure can also produce high gap acidosis because impaired kidneys cannot clear acid effectively. As kidney function worsens, acid retention and accumulation of unmeasured anions may increase the gap while bicarbonate declines. That is why kidney markers and the chemistry pattern must be interpreted together.
A low bicarbonate value alone does not tell you which pattern is present. The anion gap tells you whether the process is likely driven by chloride replacement or by hidden acids. That distinction is central to good lab interpretation and to prioritizing the next tests.
Typical Causes of Reduced Bicarbonate
Several states can reduce bicarbonate, and the anion gap helps group them into probable categories. A frequent cause is diarrhea, which results in direct bicarbonate loss from the gastrointestinal tract. This typically creates a normal anion gap metabolic acidosis because chloride rises to maintain electrical neutrality.
Ketoacidosis is an additional important cause. It creates a high anion gap metabolic acidosis because ketone bodies act as unmeasured acids. The same logic applies to lactic acidosis, where lactate accumulates and bicarbonate is consumed in buffering the acid load.
Renal tubular acidosis is a classic cause of low bicarbonate with a normal anion gap. The kidneys either cannot acidify urine properly or cannot reclaim bicarbonate efficiently. This impairs acid-base balance without necessarily increasing unmeasured anions.
Chronic kidney disease can contribute to both normal and high gap patterns depending on severity and stage. In earlier phases, patients may have a normal gap acidosis from impaired acid excretion. In more advanced disease, retention of unmeasured acids can widen the gap. That is why chronic kidney disease requires close attention to the full clinical picture and trend over time.
Other contributors may include medications, toxin exposures, or mixed disorders, but the major causes above are the most common first steps in a clinical evaluation. The key is to connect the bicarbonate result to the anion gap and then choose the next test based on that pattern.
Step-by-Step Clinical Interpretation
A careful interpretation commences with verifying that the low bicarbonate is actual and clinically important. Initially, review the chemistry panel and look at the complete electrolyte pattern. Next assess whether the finding aligns with the patient’s symptoms, history, and overall clinical assessment.
If the bicarbonate is low, ask whether an arterial blood gas or venous blood gas is needed to confirm acid-base status. A blood gas can distinguish metabolic acidosis from respiratory disorders and can help detect mixed abnormalities. Any blood gas may be useful depending on the clinical setting and the level of detail required.
Next, calculate or review the anion gap. If the gap is high, think about unmeasured acids such as lactate or ketones. If the gap is normal, think about bicarbonate loss, renal tubular defects, or GI loss. Then use the delta gap to look for mixed acid-base disorders when the numbers do not support a single explanation.
The delta gap compares the rise in anion gap with the fall in bicarbonate. If the change is disproportionate, there may be more than one acid-base process occurring at the same time. This is an important part of a refined diagnostic workflow because mixed disorders are common in acutely ill patients.
A practical sequence is:
- Verify the low bicarbonate on the serum chemistry panel. Assess serum sodium, serum chloride, and albumin. Work out the anion gap and consider albumin correction. Use arterial blood gas or venous blood gas if confirmation is needed. Assess for delta gap and mixed disorders. Arrange follow-up testing based on the most likely cause.
This approach turns a single abnormal lab result into a structured acid-base evaluation rather than a guess.
When Extra Evaluation Is Required
Extra workup is appropriate when the low bicarbonate result is unexplained, severe, ongoing, or paired with concerning symptoms. Typical follow-up studies include lactate, ketones, creatinine, and formal blood gas analysis. Each study helps clarify the cause of the acid-base abnormality.
Lactate is important when tissue hypoperfusion, infection, hypoxia, or shock is possible. Elevated lactate supports lactic acidosis and helps explain a high anion gap. Ketones are useful when diabetes, fasting, alcohol use, or poor intake might be contributing to ketoacidosis.
Creatinine helps measure renal function and can reveal whether reduced kidney clearance is contributing to metabolic acidosis or to a high gap pattern. When kidney function is worsening, the result interpretation should take into account the https://anion-gap-widget398.theburnward.com/what-could-be-the-symptoms-of-high-anion-gap-acidosis broader trajectory of the illness.
Blood gas analysis becomes especially useful when the chemistry panel and the clinical picture do not match. It can clarify pH, carbon dioxide, and compensation status, which is important when deciding whether the patient has a simple metabolic issue or a mixed respiratory-metabolic disturbance.
Extra testing is also warranted if albumin is low, because the albumin-corrected anion gap may reveal a hidden high gap process. In that situation, routine lab interpretation can miss clinically important acid accumulation unless correction is applied.
Common Questions Regarding Anion Gap and Low Bicarbonate
What does a low bicarbonate with a high anion gap mean?
A low bicarbonate with a high anion gap usually means high anion gap metabolic acidosis. This pattern suggests accumulation of unmeasured acids, such as in lactic acidosis, ketoacidosis, or advanced kidney dysfunction. It is a key clue that the body is buffering an acid load rather than simply losing bicarbonate.
Can bicarbonate be low with a normal anion gap?
Absolutely. A low bicarbonate level can occur with a normal anion gap metabolic acidosis, often from diarrhea, renal tubular acidosis, or some forms of kidney disease. In such situations, bicarbonate is lost or not properly regenerated, while chloride rises to keep electrical balance.
Should albumin be corrected when calculating the anion gap?
Yes, when albumin is abnormal, correcting the result is often important. Because albumin is a major unmeasured anion, low albumin can hide a true gap elevation. The albumin-corrected anion gap increases accuracy and strengthens laboratory interpretation.
What conditions commonly cause low bicarbonate?
Typical causes include diarrhea, ketoacidosis, lactic acidosis, renal tubular acidosis, and chronic kidney disease. The anion gap helps differentiate normal gap causes from high gap causes, which makes it a valuable part of metabolic acidosis assessment.
When should a blood gas be ordered after a low bicarbonate result?
A blood gas should be ordered when the bicarbonate result is unanticipated, severe, persistent, or accompanied by symptoms suggesting a significant acid-base problem. Arterial blood gas or venous blood gas testing can establish the disorder, identify compensation, and provide a more accurate diagnosis when chemistry results alone are not enough.