What delta ratio means in acid-base analysis
The delta ratio is a practical way to understand the relationship between an increased anion gap and the drop in bicarbonate during assessment of acid-base disorders. It helps clinicians decide whether a patient’s blood chemistry fits a straightforward metabolic acidosis pattern or whether a mixed acid-base disorder may also be present.
In plain language, the delta ratio compares how much the anion gap has risen above normal to how much bicarbonate has fallen below normal. If both changes increase and decrease in a similar way, the pattern may suggest a single high-gap process. If the relationship is discordant, it can point to another metabolic disturbance such as normal anion gap metabolic acidosis or a simultaneous alkalosis.
This is where an Anion Gap Calculator becomes especially valuable. A calculator accelerates the initial calculation of the anion gap formula and aids better clinical interpretation of serum electrolytes. It does not override judgment, but it gives a fast starting point for patient evaluation and helps clinicians focus on the probable differential diagnosis.
The delta ratio is most informative when the main question is not just whether the anion gap is elevated, but whether the anion gap increase and the bicarbonate decrease are balanced. That relationship can show whether the patient has only one acid-base process or a more complex picture affecting acid-base balance and acid-base status.
How to determine the delta ratio in a stepwise manner
To work out the delta ratio, first determine the anion gap using an anion gap calculator or by hand. The usual anion gap formula is:
Anion gap = sodium − (chloride + bicarbonate)
Some clinicians also add potassium, depending on the method used. Because different methods may apply, it is important to know which formula your lab or tool uses before making an interpretation.
Once the anion gap is known, check it with the expected normal value. Then compare the change in bicarbonate from the expected reference range. This difference is often described as the delta gap. A common approach is:
Delta ratio = (measured anion gap − normal anion gap) ÷ (normal bicarbonate − measured bicarbonate)
Step by step, the process looks like this:
- Examine the patient’s electrolyte panel, especially sodium, chloride, and bicarbonate. Determine the anion gap or use an anion gap calculator. Determine whether the result is a normal anion gap or an elevated anion gap pattern. Check how far bicarbonate has fallen from the expected reference range. Calculate the delta ratio and interpret the relationship.
In day-to-day use, the ratio is not just a math exercise. It is a diagnostic tool that helps connect laboratory values with the patient’s likely metabolic state. For example, a patient with severe lactic acidosis may have a very different pattern than a patient with simple hyperchloremic acidosis.
Accurate measurement matters. Small errors in sodium, chloride, or bicarbonate can change the result, especially when the values are close to the cutoff. That is why many clinicians use an Anion Gap Calculator first, then assess the clinical context before concluding whether the pattern is consistent with mixed metabolic acidosis.
Delta ratio formulas and benchmark ranges
The delta ratio is based on the relationship between the expected normal anion gap and the patient’s measured elevated anion gap. The exact reference range for normal anion gap can vary by lab, technique, and whether potassium is included. That variation matters because the selected normal baseline affects the final ratio.
A commonly used interpretation framework is:
- Delta ratio less than 1: the fall in bicarbonate is more than the rise in the anion gap, suggesting a possible concurrent normal-gap acidosis. Delta ratio around 1 to 2: often consistent with isolated high-gap metabolic acidosis. Delta ratio greater than 2: may suggest a concurrent metabolic alkalosis or preexisting elevated bicarbonate.
These cutoffs are not absolute rules, but they offer a practical clinical interpretation. The ratio is best seen as a guide to the acid-base pattern rather than a standalone diagnosis.
Because the anion gap changes with serum albumin, an albumin-corrected anion gap may be https://anion-gap-tool758.yousher.com/can-the-anion-gap-change-with-lab-method needed. Albumin is a major unmeasured anion, so low serum albumin can make the anion gap appear falsely normal or only mildly elevated. Correcting for albumin can uncover a hidden high-gap process and improve the accuracy of the delta ratio calculation.
In other words, when albumin is low, the raw anion gap may underestimate the real disorder. Using the corrected value is often necessary for reliable acid-base interpretation, especially in complex patients with multiple metabolic issues.
Interpreting delta ratio results
The delta ratio is especially useful when you already suspect metabolic acidosis and want to know whether there is a single issue or another process too. A high anion gap by itself suggests an accumulation of acids, but the delta ratio shows you whether the bicarbonate response is in line.
When the ratio is in the expected range, the picture may suggest a more straightforward high anion gap metabolic acidosis. Common causes include lactic acidosis, ketoacidosis, and renal failure. In these situations, the anion gap increase and bicarbonate decrease tend to rise and fall together in a predictable way.
If the delta ratio is low, the bicarbonate decrease is larger than expected for the amount of gap increase. This can suggest a second process, often normal anion gap metabolic acidosis such as diarrhea or renal tubular acid loss. In practice, this means the patient may have mixed acid-base disorder rather than just one problem.

If the ratio is high, the patient may have an additional alkalinizing process, such as vomiting or prior bicarbonate retention, which may obscure the full degree of acid load. That is why clinical interpretation should always include the patient’s symptoms, medications, and overall condition.

For example, a patient with ketoacidosis can also have volume contraction and vomiting, which may create a mixed picture. Another patient with lactic acidosis and chronic diuretic use may show a ratio that reflects both acid accumulation and metabolic alkalosis. These patterns matter because they change treatment priorities and monitoring strategy.
The key idea is that the delta ratio helps answer this question: is the bicarbonate drop explained only by the high-gap process, or is there another metabolic disturbance present? That is a core step in differential diagnosis and patient evaluation.
Typical clinical presentations and what they suggest
Several recurring presentations make the delta ratio especially useful in bedside assessment. One common pattern is hyperchloremic metabolic acidosis, sometimes referred to as normal-gap acidosis. In this context, bicarbonate is low, chloride is relatively high, and the anion gap may remain normal. Should a patient has both a high-gap process and hyperchloremic acidosis, the delta ratio may fall below the expected interval.
Another important pattern is the relationship between the acid-base disorder and respiratory compensation. The body often responds to metabolic acidosis by increasing ventilation to lower carbon dioxide. This compensatory change can help stabilize pH, but it does not fix the primary metabolic problem. The delta ratio focuses on the metabolic part of the disorder, while respiratory compensation must be assessed separately.
Correction for albumin is another common clinical step. Since low serum albumin can lower the baseline anion gap, failing to adjust for albumin can cause the clinician to miss a hidden elevated gap process. That is especially relevant in hospitalized patients, where malnutrition, inflammation, or fluid shifts may alter serum albumin.
Some frequent pattern combinations include:
- High-gap acidosis with an expected delta ratio: typically indicates a dominant cause such as lactic acidosis, ketoacidosis, or renal failure. High-gap acidosis and a low delta ratio: may suggest concurrent hyperchloremic acidosis. High-gap acidosis and a high delta ratio: may suggest a mixed disorder with metabolic alkalosis or chronic bicarbonate elevation.
These combinations can guide the next steps in the diagnostic process. For example, in suspected renal failure, the ratio may help distinguish a pure uremic acidosis from combined disturbances. In suspected ketoacidosis, it may reveal whether vomiting or treatment effects are also shaping the blood chemistry.
Constraints in the delta ratio in use
Although the delta ratio is useful, it has clear limitations. It relies on accurate laboratory values, and minor variations in measurement can change the final interpretation. Lab variability can affect sodium, chloride, and bicarbonate values sufficiently to shift the ratio across a threshold.
Measurement error is another concern. Various analyzers, sample handling issues, and timing of blood draws can all affect the numbers. When the values are borderline, even a slight discrepancy can lead to a misleading conclusion.
The ratio also depends on the chosen normal baseline. Because the expected anion gap and bicarbonate range vary by laboratory, the calculated delta ratio is not universal. That is why the exact reference range used by the Anion Gap Calculator or the clinical team should be known before interpreting the result.
Most importantly, the delta ratio should never replace clinical context. Symptoms, medication history, kidney function, lactate levels, ketones, fluid status, and respiratory pattern all matter. A number alone cannot diagnose the cause of the acid-base disorder.
For this reason, the best use of the delta ratio is as part of a broader acid-base review. It helps structure the laboratory values, but the final interpretation should come from the entire patient context, not from the ratio by itself.
When to use an anion gap calculator for assessment
An anion gap calculator is most useful when you want a quick and consistent way to review serum electrolytes during acid-base analysis. It lowers manual errors and makes it easier to assess whether the pattern suggests high anion gap metabolic acidosis or another disorder.
You may want to use a calculator when reviewing:
- Unexpected changes in sodium, chloride, or bicarbonate Suspected metabolic disturbance during patient evaluation Potential acid-base imbalance in a patient with renal failure, sepsis, diabetes, or toxin exposure Cases where the raw anion gap needs albumin-corrected anion gap interpretation
Because the calculator arranges the initial numbers, it can improve the speed and quality of clinical interpretation. This is especially helpful when the clinician is reviewing a differential diagnosis and needs to decide whether the blood chemistry suggests lactic acidosis, ketoacidosis, mixed metabolic acidosis, or another cause.
The calculator is also useful when potassium is part of the calculation method. Although potassium usually contributes less than sodium, including it can marginally change the result. That matters in edge cases and when the anion gap is near the normal range.
Ultimately, the Anion Gap Calculator should be viewed as a diagnostic tool that assists interpretation, not a stand-in for judgment. It helps identify whether the anion gap is normal or elevated, whether bicarbonate is disproportionately low, and whether the pattern might indicate a mixed disorder.
FAQ on delta ratio and anion gap assessment
What exactly is the delta ratio in anion gap assessment?
This ratio compares the rise in the anion gap to the decrease in bicarbonate. It helps determine whether a patient’s metabolic acidosis is likely one isolated high-gap process or a mixed acid-base disorder. In practice, it improves acid-base diagnosis by showing whether the laboratory values change in a corresponding way.
How is calculated the delta ratio from anion gap and bicarbonate values?
First compute the anion gap using the anion gap formula: sodium minus chloride plus bicarbonate. Then subtract the normal anion gap from the measured anion gap, and divide that by the normal bicarbonate minus the measured bicarbonate. An Anion Gap Calculator can streamline the calculation and lower errors in interpretation.
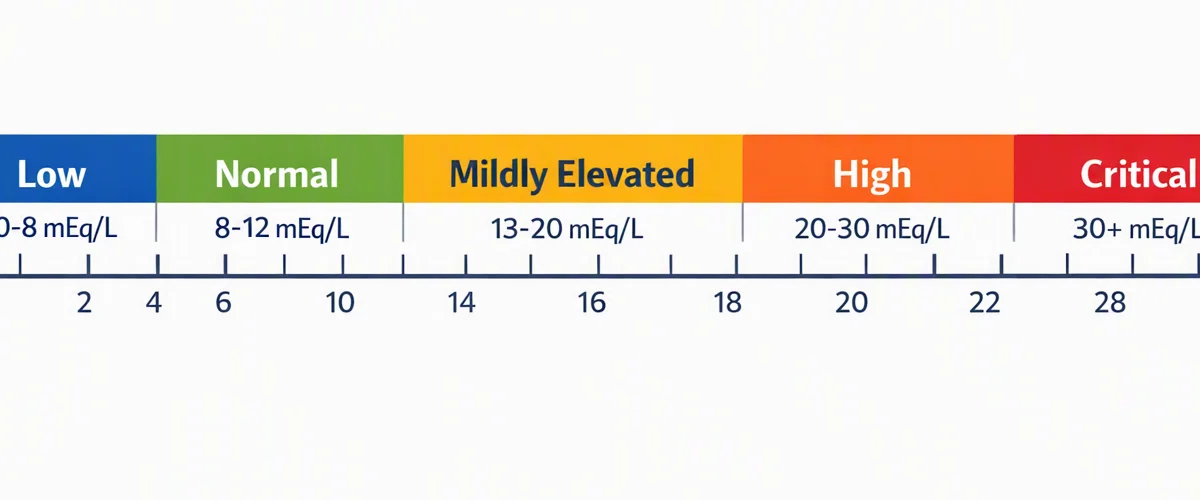
What does a high or low delta ratio?
A low delta ratio may indicate that bicarbonate has fallen more than expected, which can point to a concurrent normal anion gap metabolic acidosis such as hyperchloremic acidosis. A high delta ratio may indicate an additional metabolic alkalosis or another factor raising bicarbonate. A ratio in the expected range often fits a more isolated high-gap metabolic acidosis.
When should an albumin-corrected anion gap?
An albumin-corrected anion gap should be used when serum albumin is low or when the clinical picture does not match the uncorrected result. Because albumin is a major unmeasured anion, low albumin can mask an elevated anion gap. Correcting for albumin increases the accuracy of the acid-base assessment.
Is it possible for the delta ratio reveal mixed acid-base disorders?
Yes. One of the main uses of the delta ratio is to help detect a mixed acid-base disorder. If the relationship between anion gap increase and bicarbonate decrease is not what you would expect for a single disorder, it may indicate mixed metabolic acidosis, metabolic alkalosis, or another concurrent process. It is best used alongside clinical context, respiratory compensation, and the full electrolyte panel.